
A swelling on the gum beside a tooth has two quite different possible origins, and they need opposite treatments. Getting the distinction right is one of the more consequential calls in dentistry.
Here is how a gum-origin problem differs from a tooth-origin one, the tests that separate them, and what happens when it turns out to be both.
Key takeaways
- A periodontal problem starts outside the tooth; an endodontic one starts inside it.
- Pulp testing is the single most useful test — a tooth that responds normally to cold is rarely the source.
- Deep, narrow probing depths point to a periodontal origin; a sudden swelling with a dead pulp points to endodontic.
- Sometimes both are present, and the order of treatment changes the outcome.
Two different problems that look alike
Both produce swelling, tenderness, a bad taste and sometimes pus. What differs is where the infection began.
A periodontal problem starts in the tissues around the tooth — gum, ligament and supporting bone — usually where a deep pocket has trapped bacteria. The tooth itself may be entirely healthy inside.
An endodontic problem starts inside the tooth. The pulp dies, infection travels out through the root tip, and finds a route to the surface through the gum. The gum is where you see it, not where it began — our abscess guide covers that in detail.
How they differ in practice
| Feature | Periodontal | Endodontic |
|---|---|---|
| Pulp response to cold | Normal — the tooth is alive | No response — the pulp is dead |
| Probing depths | Deep and wide, often several sites | Normal, or one narrow deep track |
| Other teeth affected | Frequently — it is usually generalised | Almost always a single tooth |
| Swelling position | Beside the tooth, nearer the gum margin | Nearer the root tip, higher in the gum |
| Tooth mobility | Common, from bone loss | Unusual unless the infection is extensive |
| Onset | Gradual, with a history of gum disease | Often sudden, sometimes after a period of toothache |
| History of decay or a big filling | Not necessarily | Usually |
Swipe the table sideways to see every column.
The tests that settle it
Pulp testing does most of the work. Cold is applied briefly and we watch how the tooth responds compared with its neighbours.
A normal response means a living pulp, which makes an endodontic origin unlikely. No response at all means a dead pulp, which makes it very likely. That single test resolves a large majority of cases in under a minute.
Probing adds the second half. A fine probe is walked around each tooth measuring the gum attachment. Generalised deep pockets across several teeth indicate periodontal disease; a single narrow deep track beside an otherwise healthy gum is usually an endodontic infection draining out.
What the gum tells you on its own
Some signs point at the gums before any test. Bleeding when you brush, gums that have receded across the mouth, visible tartar and persistent bad breath are features of periodontal disease rather than of one dying tooth.

Conversely, a single tooth that has been aching, is sensitive to hot, or has darkened, with healthy gums elsewhere, is telling you the problem is inside that tooth — see what sensitivity patterns mean and why a tooth darkens.
When it is both
Combined lesions exist, and they are the reason this distinction gets its own literature. An endodontic infection draining down the side of a root can create a pocket that then behaves periodontally; advanced periodontal disease reaching the root tip can compromise the pulp.
The practical rule is to treat the endodontic component first. A tooth with a dead pulp will not respond to periodontal treatment while the source is untreated, whereas resolving the pulp infection frequently allows the associated pocket to heal on its own. Reversing that order wastes months.
Why the distinction matters so much
The treatments have almost nothing in common. Periodontal disease is managed by cleaning below the gum, sometimes surgically, plus daily control at home — a long-term maintenance problem.
An endodontic infection is resolved by treating the inside of the tooth once. No amount of scaling reaches a dead pulp, and no amount of root canal treatment fixes a deep periodontal pocket.
Prognosis differs too. A tooth with an endodontic problem and healthy support has an excellent outlook. A tooth that has already lost most of its bone support has a poor one regardless of what is done inside it — which is one of the situations where extraction is the honest recommendation.
What each one actually needs
| Periodontal origin | Endodontic origin | |
|---|---|---|
| Treatment | Cleaning below the gum, sometimes surgically | Root canal treatment |
| Number of visits | A course, then ongoing maintenance | Usually one, occasionally two |
| Your role afterwards | Daily control is decisive | Normal brushing; nothing special |
| Who provides it | General dentist or periodontist | Endodontist or general dentist |
| Outlook | Depends on remaining bone support | Good where support is intact |
| If left untreated | Progressive bone loss, eventual mobility | Abscess, then spreading infection |
Swipe the table sideways to see every column.
The column that surprises people is the third row. Periodontal disease is controlled rather than cured, and how well it is controlled depends largely on what happens at home between appointments. An endodontic infection is dealt with once and does not come back if the tooth is properly restored.
What to do if you have a swelling now
Get it looked at rather than self-diagnosing. Both origins are treatable and both worsen if left, and the tests take minutes.

Go the same day if the swelling is spreading, you have a fever, or the area near your eye or throat is involved — that is covered in the emergency guide and applies whichever the origin. The American Academy of Periodontology’s information on gum disease covers the periodontal side in more depth.
Frequently asked questions
Can a gum infection kill the nerve in a tooth?
It can, though it is the less common direction. Severe periodontal disease reaching the root tip can affect the pulp through the small openings there. The reverse — an infected pulp draining out through the gum — is seen far more often.
Why does the swelling keep coming back after antibiotics?
Because antibiotics treat the infection but not its source. If the source is a dead pulp, the tooth needs root canal treatment; if it is a deep periodontal pocket, that pocket needs cleaning. Either way the swelling returns once the course ends.
Does it matter which one it is if both need treating?
Very much. The order changes the outcome. Where the pulp is the origin, treating it first often lets the gum problem resolve on its own; treating the gum first while the source is untreated achieves little.
Will an X-ray show which it is?
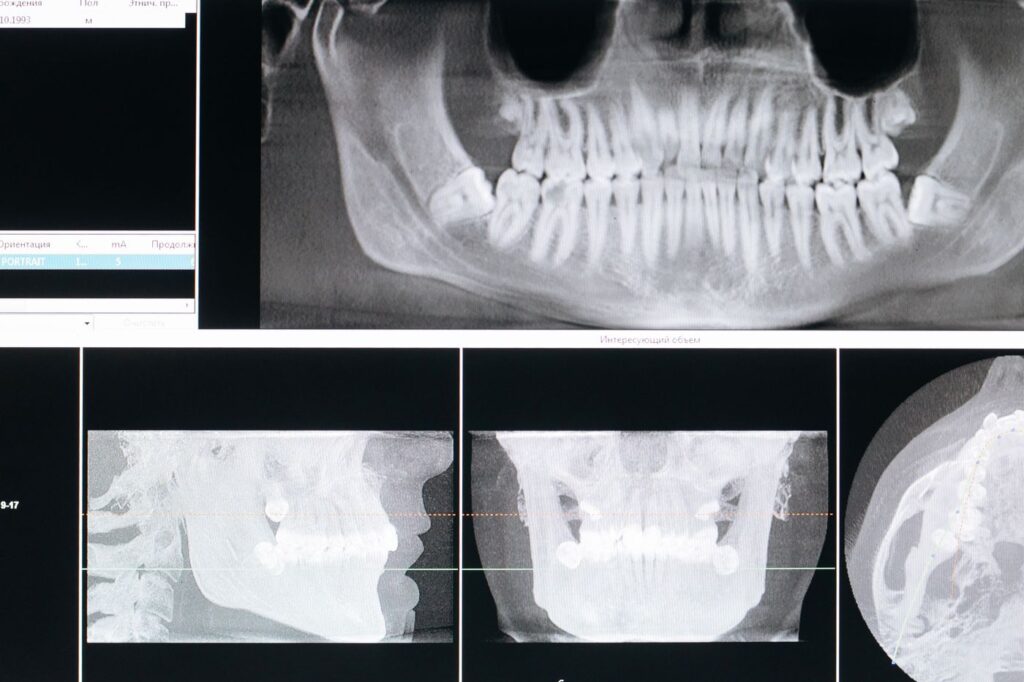
It helps but rarely decides it. Bone loss patterns differ, but early changes are subtle and both conditions can produce similar shadows. Pulp testing and probing depths carry more weight than the film.
Have Questions or Ready to Schedule?
Our team is here to help — call, email, or request an appointment online.


